Pages

Showing posts with label Verve Therapeutics. Show all posts

Tuesday, June 17, 2025

CRISPR Stocks in Wake of Verve Therapeutics Acquisition by Eli Lilly


Last night, news broke that pharma giant Eli Lilly was in talks to acquire Verve Therapeutics.  After a 3-year lull in major CRISPR dealmaking following the Covid bubble, this brings the space the Big Pharma validation that genome editing is not a crazy fantasy, but a core modality of future drug innovation. To my surprise, even hardcore biotech investors had been waiting for such validation before considering the space investable. 

Needless to say, the news will trigger pin action in other CRISPR stocks.  In this blog post, also based on a similar experience I had in the RNAi space about 10 years ago, I will lay out how I see it play out,  

Verve acquisition is a steal

As you will remember, Verve is developing an exciting one-time PCSK9 base editing treatment, VERVE-102, that could transform LDL-cholesterol-driven atherosclerotic cardiovascular disease (ASCVD).  According to the rumors in the Financial Times the proposed acquisition price is ~$1.3B.  This would be a bargain considering the potential of VERVE-102. 

Even with the current small available safety dataset, it is hard for me not to see VERVE-102 as a highly compelling option for the 1-2 million heterozygous familial hypercholesterolemia (heFH) population in the US and Europe alone.  Slap on that a $100,000 treatment price, this alone has Glp1-type market dimensions.

Under normal market conditions, such a steal would not be possible.  But these have been anything but normal biotech investment times. I believe that more than the nice short-term financial reward of an acquisition, Verve management is doing here what is best for VERVE-102 reaching its maximal potential.  Ultimately, it takes the financial resources, experience, and credibility of a pharma giant to develop and commercialize such a revolutionary treatment to such a big market.  

Who is next?

But luckily for investors, Verve Therapeutics has not been the only severely undervalued CRISPR company.  When Alnylam started to gain tremendous traction in 2012-3 after demonstrating that you can make RNAi gene silencing work in humans, still working as a consultant to companies and investors back then, I noticed how funds started to dig into who could be the next Alnylam to invest in.

So on the back of very strong recent clinical data in the space (VERVE-102, NTLA-2001/2, BEAM-302) and now the Big Pharma validation, I expect the same dynamic to unfold here.

Intellia Therapeutics

The first obvious company to benefit from fund inflow should be Intellia Therapeutics.  Verve Therapeutics will be acquired mostly for a therapeutic candidate that has shown promise in the clinic. Intellia therefore with not just one, but three clinically validated market opportunities (ATTR-CM, ATTR-PN, HAE) and a reasonably large market cap of around $900M and good trading liquidity for funds to take needle-moving positions in, will come first on the radar.

What is more, almost the entire market cap can be accounted for by its cash position and the stock has come down from a high of around $200 4 years ago to $9.  The main reservation by the investor community has been that patients will prefer a daily pill over a futuristic-sounding lifetime treatment, if not cure.  I guess they were wrong.  Not only is Eli Lilly’s proposed acquisition a vote of confidence in CRISPR modality, but the KOLs in the ATTR and HAE field are already fully on board.

Beam Therapeutics

Beam with a market cap about 2x of Intellia’s will also come into investor focus.  While I do have a small position in that company, it is by far not as big as the one I have in Intellia.

This is because I consider uncertainties around its two lead candidates, for sickle cell disease (SCD) and alpha-1-antitrypsin disease (AATD), to be higher than for Intellia’s opportunities.  Their sickle cell disease base editing should be superior to that of already approved Casgevy by Crispr Therapeutics and Vertex Pharmaceuticals. 

But will that be enough for the ex vivo autologous hematopoietic stem cell approach to gain quicker commercial traction than Casgevy?  With regard to BEAM-302 for AATD, I am still waiting for more clarity on the liver safety of their (non-GalNAc) LNP.  It was the new safety standard set by VERVE-102 (GalNAc-targeted and ‘Novartis ionizable lipid’) that makes VERVE-102 a viable therapeutic in the first place.

Prime Medicine

Having just cured p47phox variant chronic granulomatousdisease (CGD) which could entail a valuable priority review voucher, Prime Medicine is now focusing on the relatively large severe genetic liver disease opportunities of Wilson’s Disease and AATD.

While not as clinically advanced as Beam Therapeutics, Prime Medicine has the benefit of learning from the LNP safety of the Intellia, Beam, and Verve programs.  I therefore expect them to bring forward a lower-risk GalNAc-enabled LNP similar to Verve’s when it enters the clinic next year.

From a platform point of view, prime editing is the future of CRISPR medicine due to its versatility and exquisite on-target specificity.  Prime Medicine with a dominant IP position in prime editing, a market cap of $200M, much of which in cash, is therefore a prime candidate for a Big Biotech/Pharma looking to make use of that technology for its in-house targets.

Metagenomi

Going nowhere in its clinical pipeline, but generating new, especially smaller CRISPR editors that could have delivery and immunologic advantages, is Metagenomi.  Its lead candidate is a CRISPR-enabled gene drop-in approach for hemophilia A (MGX-001) which it hopes to bring into the clinic in 2026.

While I consider Metagenomi’s gene drop-in data to be industry-leading, there are questions around its safety profile since it will involve not only LNP, but also AAV for systemic delivery.  So while MGX-001 could be the first ‘gene therapy’ for hemophilia with sustained transgene expression, Metagenomi’s valuation will unlikely get recognition for it until actual clinical data.

The main reason why Metagenomi is interesting here is that it is not only trading 70% below cash ($55M market cap, $200M cash), but that it has an important partnership with Ionis Pharmaceuticals which could view CRISPR as an increasingly important mechanism to shore up its commercial ambitions in ASO-led franchises such as ATTR, HAE, and cardiovascular disease.

If I were Ionis Pharmaceuticals, I would just buy Metagenomi for $200M, retire preclinical MGX-001 for little cost and thus get rid of my future milestone and royalty obligations.  Of course, Ionis may prefer Prime Medicine for its more versatile technology.

Buying a platform-only company in this biotech tape is certainly not for the faint of heart and large funds will shy away from Metagenomic at least initially due to its small size and illiquidity.  I can see it, however, emerge as an attractive second-wave opportunity should interest in CRISPR stocks be sustained enough.  As a backstop, you still have Ionis Pharmaceuticals having to make a decision on investing further into Metagenomi later this year.

You may ask yourself why I have not mentioned the biggest CRISPR company by market cap, $3.6B CRISPR Therapeutics.  This is because of initially overoptimistic expectation for Casgevy sales and with their recent RNAi deal spreading themselves out too thinly and losing their cutting edge so early in the game.  I would also like to see them disclose the liver safety before attributing value to their first generation Cas9 nuclease-based cardiovascular CRISPR franchise.


Disclosure: Verve Therapeutics became my largest portfolio position after they disclosed VERVE-102 data two months ago.  While smaller than my positions in Huntington’s disease gene therapy company uniQure and RNA editing company ProQR, Prime Medicine and Intellia Therapeutics are not far behind and very meaningful positions with close to 10% portfolio weightings.

This is not financial advice.  It is intended for those interested in contemplating the stock market repercussions of the rumored Verve Therapeutics acquisition.  Buying a stock is the simple part, successfully trading it for profit much more difficult. 


Sunday, May 18, 2025

Landmark ATTR-Polyneuropathy Data by Intellia Caps Off Momentous Week in CRISPR Therapeutics

This has been a most remarkable week in CRISPR Therapeutics as momentum continues to build. 

Bespoke therapeutic in 6 months

First, the drug development world and beyond was captivated by the story of how a baby born with life-threatening point mutations in the CPS1 gene was able to receive a bespoke base editing therapy in just 6 months by harnessing the platform potential of nucleic acid-targeted therapeutics and regulators getting out of the way (Musunuru et al 2025). 

Every pharma CEO will be asking her business development underlings about recent underinvestment in the technology when the report shows how development timelines and expenses can be slashed by a factor of 10 when everybody applies ‘common sense’.


I purposely make use of new US administration lingo, because while the CPS1 deficiency story happened under the watch of Peter Marks who was fired as CBER chief because of his involvement in Covid19 mRNA vaccines, there is every reason to believe that drug development will continue to be streamlined by cutting out time-consuming bureaucratic hurdles and applying AI-based document reviews.  Accordingly, Trump's HHS and FDA has repeatedly called for accelerated drug development based on common sense, including biological plausibility.  As further evidence of that, it is phasing out certain lengthy animal toxicology studies.

The most immediate beneficiaries of the story are nucleic acid-targeted therapeutics addressing severe, underserved diseases by harnessing proven delivery and which have a clean off-target profile.  Besides CRISPR-based therapeutics, this also includes oligo-mediated RNA editing which has exquisite on-target specificity and where Rett Syndrome could serve as a template when addressing disease populations segmented by numerous mutations.   


First patient treated with prime editing medicine

Though behind a paywall, STAT reported last week that the first patient had been treated with a CRISPR prime editing agent.  The timing is fitting, as prime editing, by virtue of it being able to address any small mutation, including non-transition mutations and small deletions, is the most universal iteration of CRISPR.  It is also the safest of them all with Prime Medicine claiming no detectable off-targeting for any of its development candidates.

The CPS1 urea cycle story could have been even better if they had used the safer and more effective delivery of VERVE-102 instead of VERVE-101 used by former Verve employee and co-founder Kiran Musunuru.  Also, the base editor in question had not been tested before in the clinic and was selected by comparing a number of adenine base editors in cell lines which also differed in terms of PAM sites and bystander editing.  A prime editing approach by contrast is not subject to PAM constraints as the edit can happen well within a 50 nucleotide window of a given PAM without losing much efficacy.  There is also no bystander editing to worry about.  This way, the same (proven) prime editor mRNA could be used in the same LNP formulation.

The key to quickly applying prime editing in such circumstances would be (AI/machine) learning from the growing dataset of prime editing experiments to find guide RNAs of high efficacy.

Prime Medicine has made great strides towards getting editing efficiencies up to standard Cas9 and base editing levels.  With the first patient dosed, we can expect data in support of that well before the end of the year (2 months for engraftment in the CGD setting).


CRISPR Therapy sets new standard in ATTR-Polyneuropathy

And as if all this was not enough, Intellia today reported 2-year data from their phase I/II study of its Cas9 CRISPR agent NTLA-2001.  Unlike prior TTR knockdown agents by Alnylam (RNAi) and Ionis (RNaseH antisense), key mNIS+7 and Norfolk quality of life measures show that after 2 years of sustained -90% TTR reductions, NTLA-2001 not only stabilizes patients, but the majority of patients improve.  In the dose expansion cohort, there was a clinically highly impactful -8.5 point improvement in mNIS+7. 


Clinically meaningful >4 point improvements were also seen in 5 out of the 6 patients that had been on an RNAi treatment (Patisiran) before.  It is also an improvement over what had been observed at the 12-month timepoint before with NTLA-2001 and sends a strong message:

A one-course treatment permanently changing genetics for the better leads to superior outcomes as the body itself becomes the healing agent. 

I look forward to seeing histology data looking at TTR deposition and whether they start to disappear as the balance shifts towards clearance.

The superior outcome may not come as a surprise when considering that with a 90% gene knockout efficacy, NTLA-2001 halves the amount of TTR being produced following therapy compared to what knockdown agents have been able to achieve.  Still, the fact that improvements seem to accelerate over time is remarkable.

Concordantly, there were no new adverse events and illustrates that acute infusion reactions and possibly transient liver damage around LNP administration is the main safety and arguably only concern of liver-directed CRISPR therapeutics.  Safety challenges arising from having to maintain a certain level of drug concentration, which may e.g. lead to low chronic inflammation and associated transcriptionopathies, do not apply to RNA-/oligo-based CRISPR therapeutics.

With this data, NTLA-2001 should own the ATTR-polyneuropathy market, not just because of its superior efficacy and safety, but also because it is a genetically defined disease and could be given earlier, perhaps even before symptoms manifest.  This would be a hard sell from a health economics point of view for drugs that need to be taken chronically for life.  In the same vein, Intellia reported just yesterday that NTLA-2001 similarly improves the lives of people with genetic ATTR-cardiomyopathy, leading to never seen before increases in the 6 minute-walk-distance measure, not with vutrisiran and not with acoramidis.


Phase 3 studies of NTLA-2001 in ATTR-PN and ATTR-CM are ongoing and should gather steam with the new data.

It is possible that together with the recent PCSK9 data by Verve Therapeutics, last week’s developments and increased signs that regulatory flexibility will continue to be applied if not greatly accelerated by the new administration could mean that the worst for CRISPR investors could be behind.

Monday, April 28, 2025

China Fast-Follower Competition Reaches Clinical CRISPR

There is panic among Western biotech that Chinese competitors will eat their lunch with their capital-efficient fast-follower strategy which typically involves rapid clinical translation via investigator-initiated trials.  This issue has now reached the CRISPR space in the form of first clinical data announced by YolTech regarding a PCSK9 base editing trial for the treatment of hypercholesterolemia.

Almost identical to pioneer Verve Therapeutics which reported stellar data earlier this month (discussed here), YolTech’s YOLT-101 formulation involved a GalNAc-LNP encapsulating an adenine base editor mRNA and guide RNA targeting a splice site of the PCSK9 pre-mRNA for gene knockout.  The more detailed nature of the LNP formulation was not disclosed in the accompanying medRXiv publication.   

The trial tested 3 dose levels of YOLT-101: 0.2mg/kg (n=1), 0.4mg/kg (n=2), and 0.6mg/kg (n=3) indicating an unusually rapid move up in the dose level by international standards.  Efficacy was only reported for one subject treated with 0.4mg/kg and the three 0.6mg/kg subjects with heterozygous familial hypercholesterolemia.

Similar to Verve Therapeutics, LDL-cholesterol lowering was roughly -50% for 0.6mg/kg.  Unfortunately, the information provided did not allow for an analysis of the relationship of total dose of YOLT-101 and LDLc reduction.  On the PCSK9 front, YolTech seemingly did better than Verve Therapeutics reaching a mean of -76% versus the -60% for VERVE-102 both at 0.6mg/kg.


This, however, is where the similarities ended.  In terms of the critical safety of a potentially very widely applicable therapy, 3 out of the 6 subjects treated with YOLT-101 exhibited ‘transient elevations in ALT and AST’ that ‘almost’ returned to normal within one month.  Furthermore, 5 of 6 subjects experienced infusion-related reactions involving fever, myalgia, and vomiting. And similar to Verve’s ill-fated VERVE-101 formulation, one subject at the 0.4mg/kg dose experienced chest pain shortly after LNP infusion.


Nevertheless, the authors noted that the trial remains ongoing to ‘validate the therapeutic durability and safety profile’.  Considering the ALT/AST elevations for which more detailed values were not disclosed, it seems questionable whether this is an ethical decision.  Add to this the rapid dose escalation and selective data disclosures, it provides fodder to those criticizing China for allowing human experimentation and Big Pharma taking advantage of it by licensing therapeutic candidates built on such strategies on the cheap, not even mentioning the intellectual property issues of ‘Chinese Beam Therapeutics’


Tuesday, April 22, 2025

The time for genome editing is now

Back from recent CRISPR conferences in Ireland and Denmark, I wanted to share my current thinking about the present and foreseeable future of clinical genome editing.


CRISPR is a clinically mature platform

First of all, genome editing, and in particular CRISPR Therapeutics have arrived big time.  Ignore for a moment the 90%+ declines in the share prices of Intellia, Verve, and Metagenomi, that all, with the exception of perhaps Beam Therapeutics, suggest that the industry will not survive.  Focus instead on the transformational results last week by Verve Therapeutics which will shape the management of chronic metabolic and cardiovascular disease for decades to come, Beam Therapeutics last month announcing that it  for the first time fixed a genetic disease (AATD) by reversing a point mutation, or the three ongoing phase 3 programs by Intellia Therapeutics which promise patients live unintruded by their disease.

So you say that this is only half the truth and many of them will develop cancer?  With hundreds of subjects having been given CRISPR therapeutics, we still have yet to hear about such cases, including for the hematopoietic stem cell applications, probably the most stringent test in that regard given the history of retroviral gene therapy.  This is supported by ample detailed genomic analyses demonstrating that many CRISPR modalities, in particular prime editing, often do not have any detectable off-targeting (!) and therefore are safer than going out in the sun or eating grilled meat.  And don’t get me started with analysts and investors pretending that small molecule drugs, 'dirty drugs' by design, are much safer in that regard when many of them like methotrexate and hydroxyurea are known to cause cancer which barely gets a mention or is routinely accepted as part of the risk-benefit of a drug.  Similarly, the currently more widely embraced antisense and RNAi technologies exhibit considerably more off-targeting, which in theory could result in cancer development with chronic use, than the average CRISPR therapeutic candidate today. 


Prime editing is the ultimate CRISPR manifestation

Prime editing is the foreseeable endgame for genome editing involving edits up to 50 nucleotides.  This is because in addition to being able to knock out genes like (Cas9) nuclease or base editing, it allows the developer to change nucleotides at will and with incredible specificity, and for gain-of-function.  It has therefore surprised me to see that prime editing is still such a niche part in these conferences and barely used in industry and even academia where IP is less of an issue.  This can likely be explained with it requiring a good deal of mental gymnastics when devising a prime editing strategy and subsequent tinkering to optimize efficacy.  Prime editing will likely also be part of strategies for achieving even larger edits, including whole gene replacements that are often desirable.

In some ways this is reminiscent of zinc fingers which make for poor screening and quick molecular biology tools and were quickly forgotten when CRISPR came along with the promise of simple sgRNA design.  However, a panel at the Copenhagen CRISPR meeting by genome editing veterans made it clear that when optimized, zinc fingers can be every bit as powerful as CRISPR and currently have a leg up where delivery is going to be viral for some time to come.  

This is particularly true for the CNS, the fourth major tissue/organ target for genome editing applications after the liver, hematopoietic stem cell, and immune cells.  Not only is it impossible to fit in prime and base editors in single AAV vectors, expressing a CRISPR effector nuclease of bacterial origin for years may be tricky (but not unsolvable) in terms of immunogenicity.  There is also some unease about having nucleases loiter around in cells for years after their job has been done.  Self-targeting/inactivation strategies may here be called for.  Zinc fingers by being small and mimicking human proteins by contrast are ready for clinical use, a fact, as the deal flow by Sangamo Therapeutics illustrates, is increasingly being recognized by the wider industry.


Genome editing versus non-permanent modalities

Another popular argument against CRISPR Therapeutics questions why one should take a ‘risk’ with permanently altering the genome when you have oligonucleotide therapeutics options that need to be administered as infrequently as every quarter, half annually, or even annually.  

While there is some application overlap between genome editing and oligonucleotide therapeutics, especially when it comes to knocking down genes, a closer look shows that the overlap is limited.  Where there is clear genetic evidence that a gene can be disabled for life without safety risks, then genome editing is the endgame, or at least capture a good portion of the market, and transient modalities may serve to de-risk the targets first.  

When it comes to bringing pathways back into finely tuned balance and/or the disease is not chronic and likely requires only temporary treatment (e.g. some cases of hypertension), transient options are preferable.  Still in other cases such as prion or Huntington’s disease where it is not clear whether it is the overall level or distribution of gene knockdown that is more important for efficacy, the preferred modality has yet to emerge from clinical studies. 


Part of the Wall Street fashion show

Wall Street is a fashion show when it comes to biotech platforms.  A little less than 10 years ago, it predicted that CRISPR would kill off the RNAi Therapeutics industry. Today, Alnylam sports a $30B market cap, about 4x that of the entire CRISPR industry combined (much of it in cash).  Of course, investing in technologies ahead of their time is fatal. The electric vehicle industry is just one example.  As I have laid out above, genome editing, however, is now and here to stay.  Having the potential to save the healthcare system money (e.g. $2M for a one-and-done HAE/ATTR treatment as opposed to $500k annually) or to lead to drastically improved outcomes (as can be predicted from chronic LDLc lowering) got to be embraced by patients, their caregivers, docs, regulators, and insurers alike.  

It's been a rough couple of years investing in development-stage, cutting-edge biotechs and current politics does not seem helpful, but if this is when it is darkest, then generational wealth awaits the survivors with the guts to hold on during a volatile comeback.  One of my two conviction bets that I look up to in this regard is therefore CRISPR therapeutic biotech Verve Therapeutics.  Uniqure, which works in the similarly unloved gene therapy arena and has a promising DNA-directed RNAi candidate for Huntington’s disease, is the other in case you were wondering.  


Monday, April 14, 2025

Verve Therapeutics Nails Cardiovascular Disease CRISPR Study

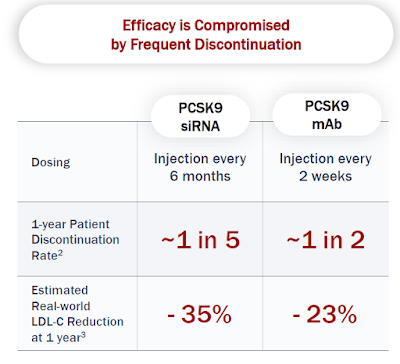
Patients do not benefit from drugs they do not take.  This is especially true in the cardiovascular disease space aimed at lowering atherogenic LDL-cholesterol where the majority of patients starting on oral options like statins do not take their pills after just one year.  This is also true for once every 2 to 4 weeks next-generation PCSK9 antibodies and even semiannual PCSK9 RNAi therapeutic inclisiran, though to a lesser degree in the latter case.


With this realization in mind, Verve Therapeutics set out to develop a PCSK9 CRISPR base editing treatment that should lower LDL-cholesterol for life by at least -40% after just a single administration of an intravenous LNP formulation.  Unfortunately, a first generation formulation, VERVE-101, had to be abandoned a year ago because of laboratory abnormalities, in particular ALT/AST elevations 5 to 10-fold above the upper limit of normal as well as a case of dangerously low platelet counts in a first clinical trial.  In addition, the intra-dose variability of the PCSK9 knockdown and LDLc lowering between subjects and the dose-responsiveness were not optimal.


Liver enzyme elevations (here ALT) with VERVE-101 in the HEART-1 study

All evidence pointed towards the LNP formulation, not the PCSK9 as the target or the base editing process, to be the culprit for the safety issues.  Verve therefore decided to replace some of the lipids in the liposomal formulation and add GalNAc sugars so as to allow the LNP to be taken up by both the LDL-receptor (via ApoE)- and ASGPR (via GalNAc).  This is helpful for two patient populations that are most in need for new treatment options and which lack LDL receptors (heFH and hoFH).  The base editor and guide RNAs were left unchanged from VERVE-101. 

Based on data from the first 14 subjects treated with VERVE-102 revealed today the theory translated perfectly into clinical practice.  At doses above 50mg of the LNP, the mean LDLc reduction was -59%, in line with the most potent PCSK9 agents (antibodies) and significantly more potent than inclisiran, especially in the heterozygous FH (heFH) population.  Moreover, there was a beautiful dose response for both PCSK9 and LDLc lowering and very little inter-patient variability.


Dose-related LDLc lowering in the HEART-2 trial with VERVE-102


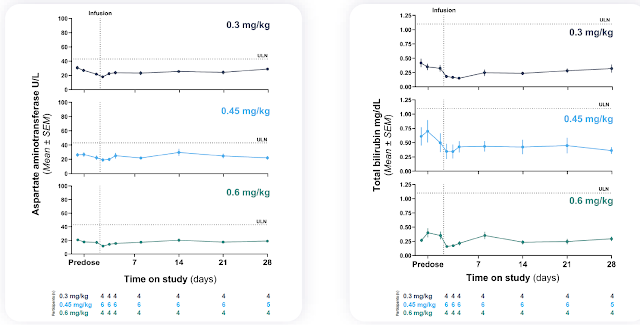
Even more importantly, the safety was pristine.  There was hardly a blip with no outliers in terms of ALT/AST changes upon LNP administration, a stark difference to VERVE-101.  Similarly, no platelet changes were seen.  Only a single case of grade 2 infusion reaction was observed which rapidly resolved and does not pose an obstacle to further clinical development and commercialization.  Anybody familiar with LNP technology understands that GalNAc-LNPs are now the gold standard in the delivery of genome editing in the liver.


Verve Therapeutics is wrapping up the HEART-2 study with a final higher dose to see whether there is further LDLc lowering and then proceed to a ~60-subject phase II study aimed at locking down one of two fixed doses of VERVE-102 for the registrational phase of clinical development.

Today marks a milestone in moving genome editing to large, indeed very large patient populations. 


Disclosure: I owned some Verve Therapeutics shares going into data and doubled down on it after seeing the emerging VERVE-102 product profile.


By Dirk Haussecker. All rights reserved.

Disclaimer: This blog is not intended for distribution to or use by any person or entity who is a citizen or resident of, or located in any locality, state, country or other jurisdiction where such distribution, publication, availability or use would be contrary to law or regulation or which would subject the author or any of his collaborators and contributors to any registration or licensing requirement within such jurisdiction. This blog expresses only my opinions, they may be flawed and are for entertainment purposes only. Opinions expressed are a direct result of information which may or may not be accurate, and I do not assume any responsibility for material errors or to provide updates should circumstances change. Opinions expressed in this blog may have been disseminated before to others. This blog should not be taken as investment, legal or tax advice. The investments referred to herein may not be suitable for you. Investments particularly in the field of RNAi Therapeutics and biotechnology carry a high risk of total loss. You, the reader must make your own investment decisions in consultation with your professional advisors in light of your specific circumstances. I reserve the right to buy, sell, or short any security including those that may or may not be discussed on my blog.